
DISRUPT BTK II CLTI Cohort Analysis
Establishing a new benchmark for patients with CLTI: New data confirm Shockwave IVL’s continued impact on patients with CLTI at 24 months. DISRUPT BTK II assessed the continued safety and effectiveness of the Shockwave Peripheral IVL System for the treatment of calcified, stenotic lesions in below-the-knee (BTK) arteries. This sub-analysis focuses on results from the patients with CLTI enrolled in the study.

CLTI Cohort Key Findings
-
Establishing a new benchmark in CLTI
Shockwave IVL delivers outcomes, out to two years, that set a new benchmark for success in the minimally invasive treatment of patients with CLTI with calcified BTK lesions. -
Demonstrating clinical durability
DISRUPT BTK II 24-month outcomes show continued durability of Shockwave IVL for calcified BTK treatment, demonstrating sustained clinical benefit in a complex CLTI population. -
Reinforcing Shockwave IVL as a frontline strategy
The 24-month outcomes further establish Shockwave IVL as a frontline calcium modification strategy for patients with complex BTK lesions.
Chandra V, Two-Year Outcomes from the Disrupt PAD BTK II Study. VIVA. Las Vegas, NV; 2026.
DISRUPT BTK II Study Design
Objective
Assess the continued safety and effectiveness of the Shockwave Medical Peripheral IVL System for the treatment of calcified, stenotic lesions in BTK arteries. Products included Shockwave M5+ and Shockwave S4.
Key Inclusion Criteria
- Rutherford classification (RC) 3-5, RC 3 capped at 20% of enrolled patients
- Moderate-severe calcification*
- Up to two BTK lesions ≤ 200 mm in length
Primary Safety Endpoint
Major adverse limb events (MALE) or post-operative death (POD) at 30 days
Primary Effectiveness Endpoint
Procedural success, defined as ≤ 50% residual stenosis for all treated target lesions without serious angiographic complications
Additional analysis to include lesions with ≤ 30% residual stenosis without angiographic complications
Independent Clinical Events Committee (CEC), Angiographic Core Laboratory, and Duplex Ultrasound Core Laboratory
DISRUPT BTK II, the largest prospective study of real-world, complex patients with moderate to severe calcified BTK disease, now demonstrates durable outcomes through 24 months.
No other calcium modification technology has been evaluated in a population this challenging, setting Shockwave IVL as a benchmark for CLTI care.
*Presence of fluoroscopic evidence of calcification by PARC (Peripheral Academic Research Consortium) definition: 1) on parallel sides of the vessel and 2) extending > 50% the length of the lesion if lesion is ≥ 50 mm in length; or extending for minimum of 20 mm if lesion is < 50 mm in length.
Full Cohort By the Numbers
Statistics Callout
This section presents key statistical information with numbers and descriptions.
-
250Patients
-
305Lesions
-
38Global sites
-
2Year follow-up

Chandra V, Two-Year Outcomes from the Disrupt PAD BTK II Study. VIVA. Las Vegas, NV; 2026.
CLTI Cohort By the Numbers
Statistics Callout
This section presents key statistical information with numbers and descriptions.
-
200Patients
-
245Lesions
CLTI Cohort Baseline Demographics
Rutherford Category
Statistics Callout
This section presents key statistical information with numbers and descriptions.
-
71%RC 5, minor tissue loss2*
-
29%RC 4, ischemic rest pain2**
Medical History
Statistics Callout
This section presents key statistical information with numbers and descriptions.
-
73%Patients had wounds at baseline2
-
18%Hemodialysis-dependent1
-
77%Diabetes mellitus1
Lesions
Statistics Callout
This section presents key statistical information with numbers and descriptions.
-
86%Moderate-severe Ca++1†
-
80mmMean lesion length1
-
31%Chronic total occlusions (CTOs)1
1: Armstrong E, One-Year Outcomes from the Disrupt PAD BTK II Study. VIVA. Las Vegas, NV; 2025.
2: Based on analysis of the CLTI cohort enrolled in the BTK II study.
*Per limb 143/201 | **Per limb 59/201 | †PARC Definition
Results and conclusion
Clinical Procedural Insights in a CLTI Cohort
In a challenging patient cohort, IVL was shown to be a safe and effective treatment of challenging calcific BTK lesions with minimal need for provisional stenting.
CONFIRMED SAFETY
| Total Serious Angiographic Complications Post-IVL2 | Total Serious Angiographic Complications at Final1 |
| 2.3% | 1.3% |
CONFIRMED EFFECTIVENESS
| Average Residual Stenosis Post-IVL2 | Average Residual Stenosis at Final1 |
| 30.0% | 25.7% |
MINIMAL PROVISIONAL STENTING
| Stent/Tack Implant Total2 | Provisional Stent/Tack Implant2 |
| 5.7% | 2.8%* |
*Remaining Stent/Tack implants were part of physicians’ standard algorithm.
1: Armstrong E, One-Year Outcomes from the Disrupt PAD BTK II Study. VIVA. Las Vegas, NV; 2025.
2: Based on analysis of the CLTI cohort enrolled in the BTK II study.
Freedom from CD-TLR at 24 Months
24-month outcomes confirm the durability of Shockwave IVL’s clinical outcomes in complex calcified BTK disease.
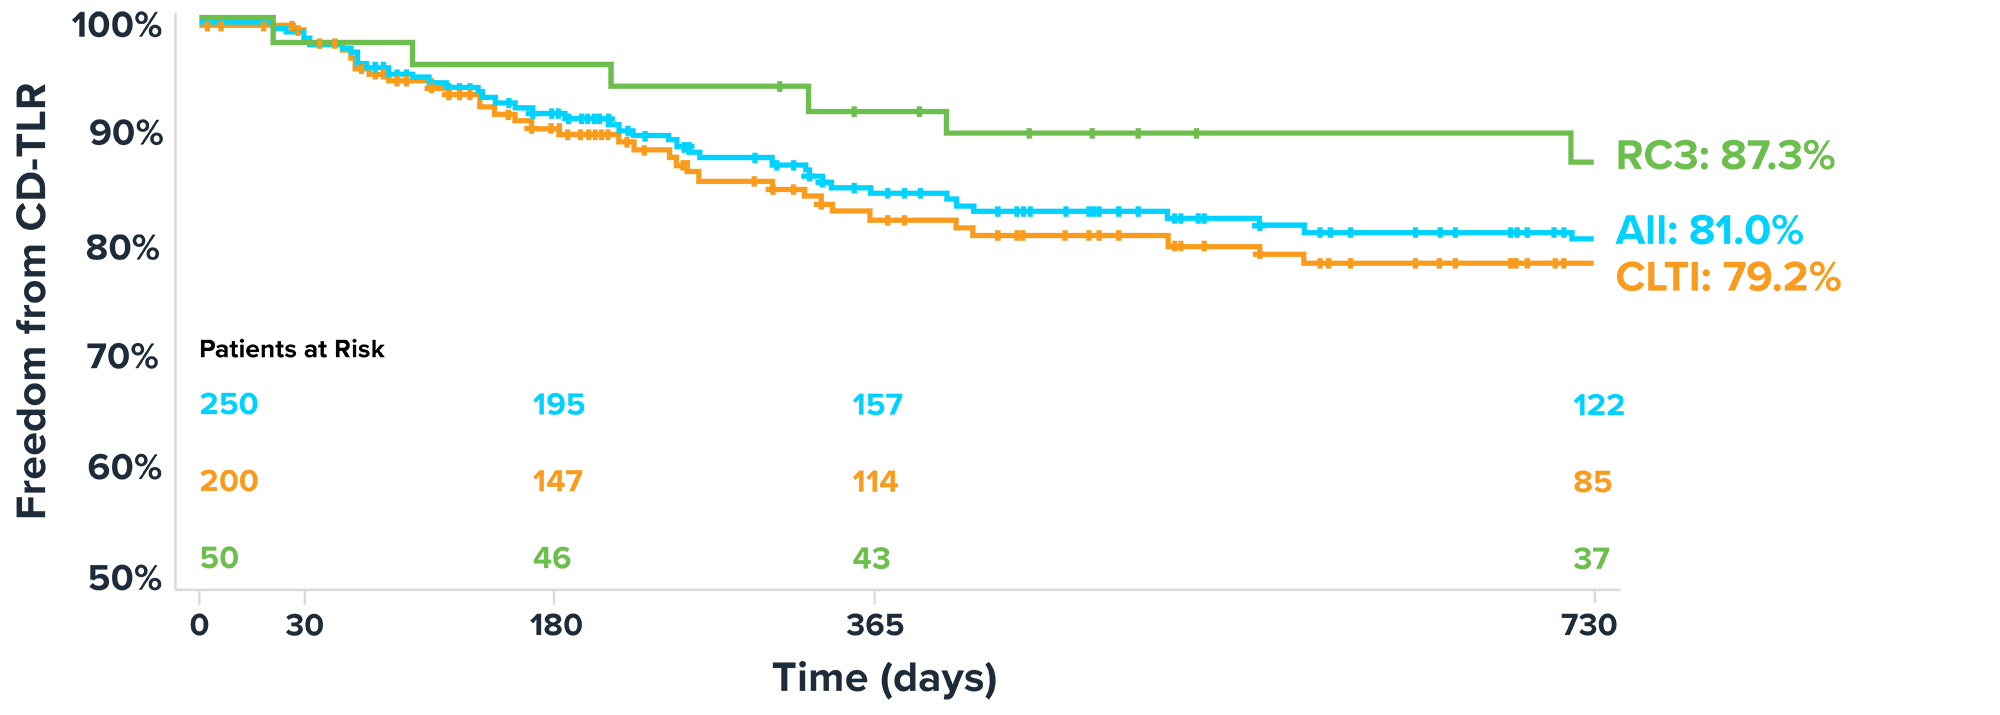
| Rutherford Category | Freedom from CD-TLR at 24 Months |
| Full Cohort (n=250) | 81.0%1 |
| RC 3 (n=50) | 87.3%1 |
| CLTI Cohort (n=200) | 79.2%1 |
| RC 4 (n=57) | 79.6%2 |
| RC 5 (n=143) | 79.3%2 |
1: Chandra V, Two-Year Outcomes from the Disrupt PAD BTK II Study. VIVA. Las Vegas, NV; 2026.
2: Data on file at Shockwave Medical.
Clinically driven target revascularization (CD-TLR).
Kaplan Meier (KM) is an analysis that uses probability to capture patients lost to follow-up.
Freedom from CD-TLR analysis excluded patients with above the ankle amputation of target limb.
Freedom from Major Amputation at 24 Months
At 24 months, Shockwave IVL supports limb preservation and sustained symptom improvement in high-risk patients with CLTI.
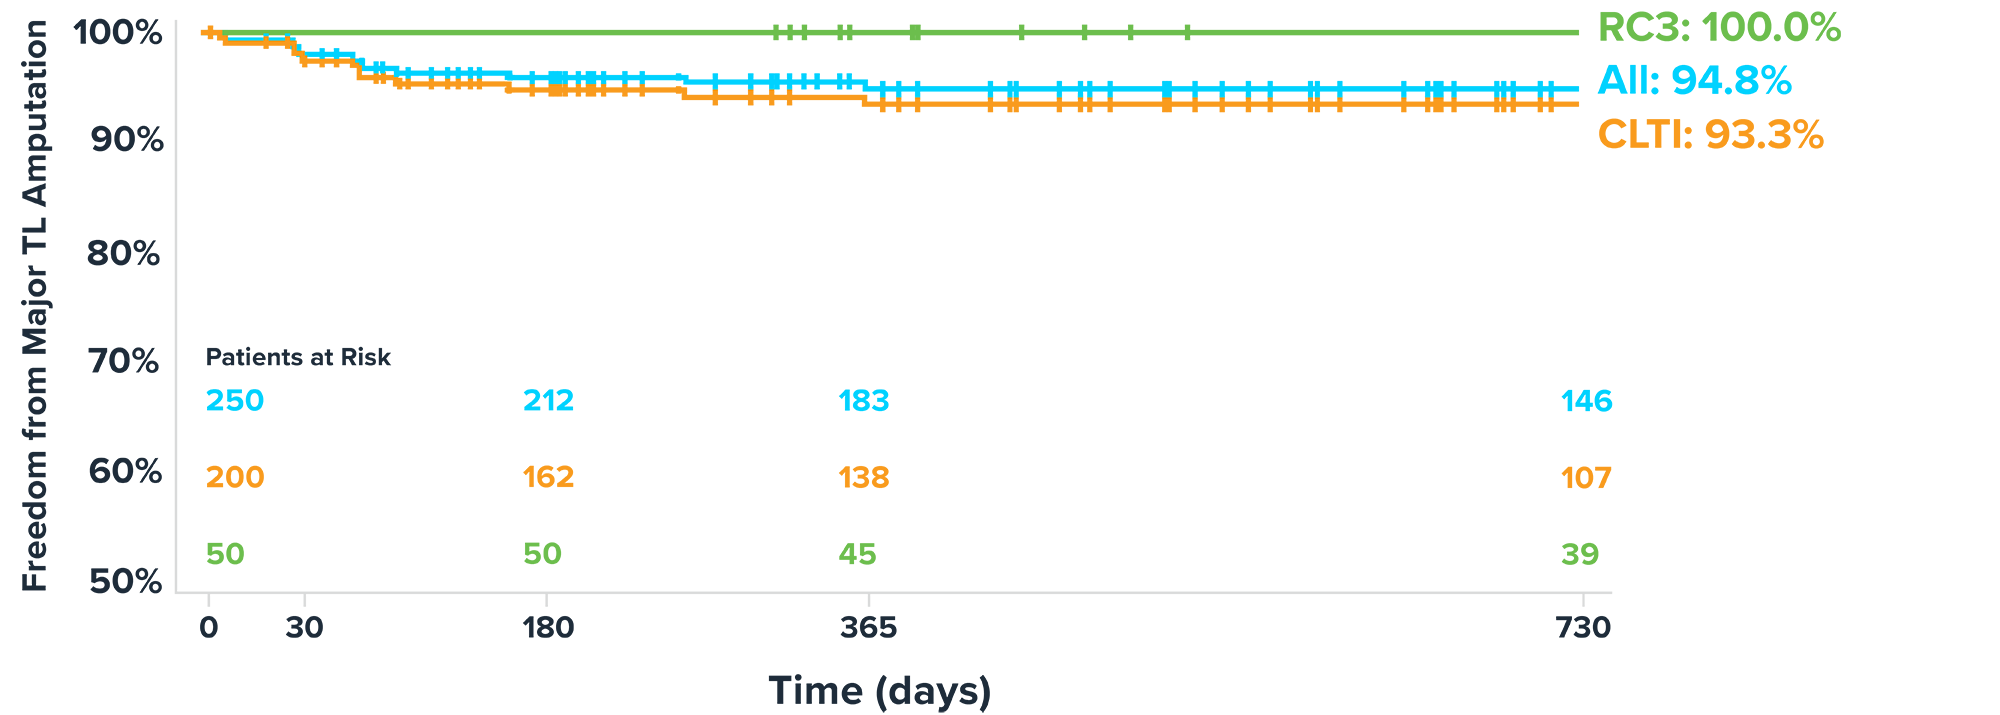
| Rutherford Category | Freedom from Major Amputation at 24 Months |
| Full Cohort (n=250) | 94.8%1 |
| RC 3 (n=50) | 100%1 |
| CLTI Cohort (n=200) | 93.3%1 |
| RC 4 (n=57) | 98.1%2 |
| RC 5 (n=143) | 91.2%2 |
1: Chandra V, Two-Year Outcomes from the Disrupt PAD BTK II Study. VIVA. Las Vegas, NV; 2026.
2: Data on file at Shockwave Medical.
Rutherford Classification (RC) Change at 24 Months
24-month outcomes show continued durability of Shockwave IVL for calcified BTK treatment, demonstrating sustained clinical benefit in a complex CLTI population.
- Of the patients remaining at 24 months, 82% were no longer CLTI1
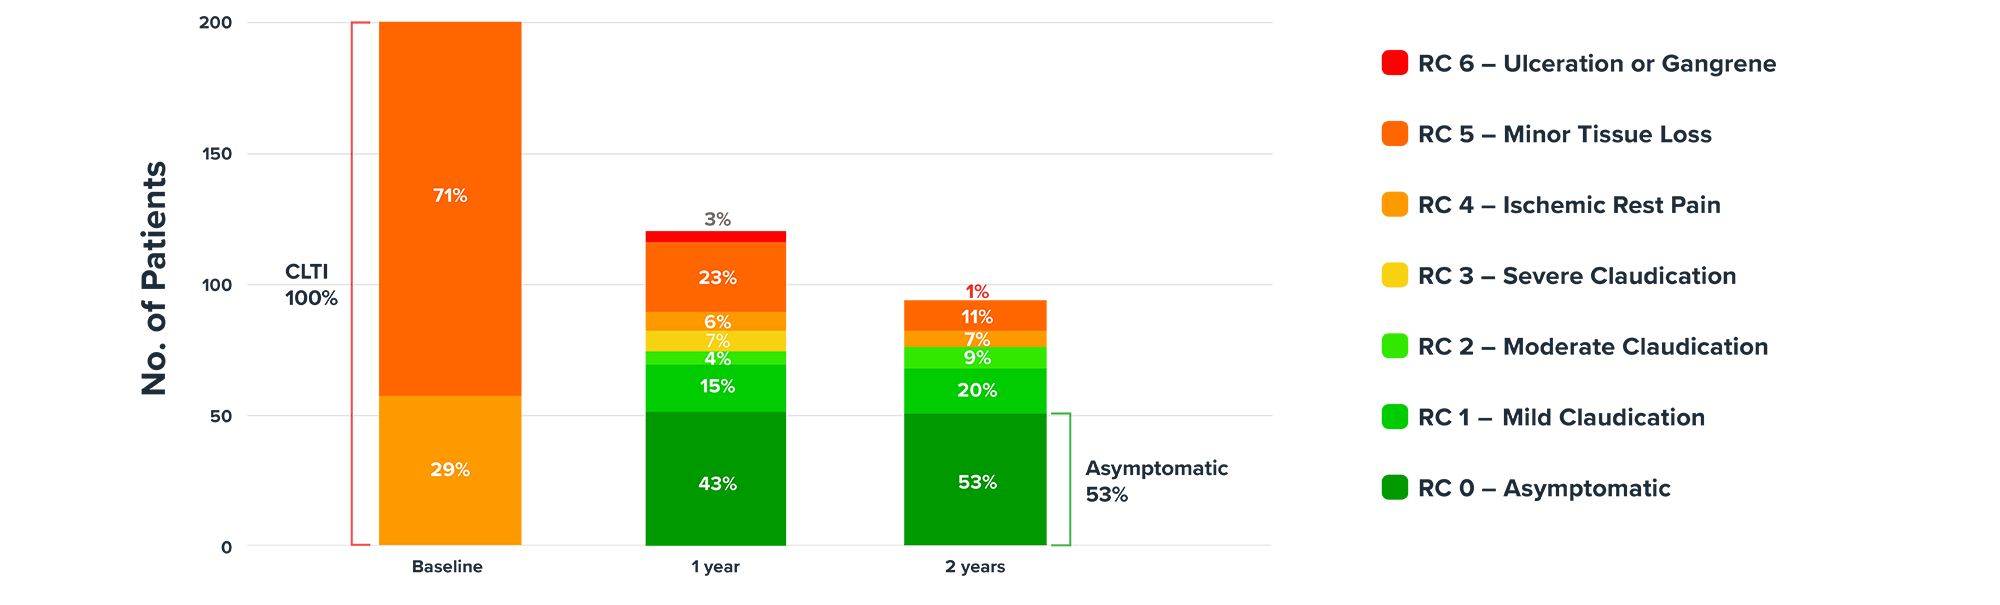
1: Chandra V, Two-Year Outcomes from the Disrupt PAD BTK II Study. VIVA. Las Vegas, NV; 2026.
Quality of Life at 24 Months
Shockwave IVL facilitates sustained symptom improvement for patients with CLTI through 24 months.
| Breakdown by Attribute | VascuQoL-6 Attribute | Activity | Tired | Walk | Concern | Social | Pain |
| Average Score 24 Months1 | 3 | 2.8 | 3.1 | 3.1 | 3.3 | 2.9 | |
| Average Score Baseline2 | 1.9 | 2.0 | 2.3 | 1.7 | 2.3 | 1.8 |
Total VascuQoL-6 Score (CLTI) at 24 months significantly improved from baseline (P-Value: p<0.001). Total at 24 months was 18.1 ± 4.6 and total at baseline was 11.9 ± 4.0.1,2
The Vascular Quality of Life Questionnaire is a survey used to determine health related quality of life (HRQoL) in patients with peripheral arterial disease (PAD). Each attribute is scored 1-4, a higher value indicates better health status. The sum of each individual attribute score is used to generate a total quality of life score.
1: Data on file at Shockwave Medical.
2: Armstrong E, One-Year Outcomes from the Disrupt PAD BTK II Study. VIVA. Las Vegas, NV; 2025.
Study Leadership
This section contains attributions including profile pictures, titles, descriptions, and Twitter handles.
-
Venita Chandra, MDClinical Associate Professor of Surgery, Associate Program Director – Vascular Surgery, Medical Director Stanford Advanced Wound Center
-
Ehrin Armstrong, MDMedical Director, Aurora Denver Cardiology Associates, Swedish Medical Center
More Shockwave Peripheral IVL Studies
-
Global prospective, multi-center, single-arm study assessing the safety and effectiveness of Shockwave peripheral IVL in treating long, calcified BTK lesions.Peripheral IVL
-
The largest-ever randomized clinical study of Shockwave peripheral IVL treatment in severely calcified peripheral lesions, out to 24 months.Peripheral IVL
-
The largest prospective real-world evidence for the treatment of complex, heavily calcified peripheral arterial disease (PAD).Peripheral IVL