Proper balloon preparation is a critical step in helping optimize procedures performed using balloon-based Shockwave Intravascular Lithotripsy (IVL) catheters.
In this step-by-step demonstration, learn how to prepare Shockwave IVL balloons for both peripheral and coronary applications using a saline and contrast mixture, three-way stopcock, syringe, and indeflator. The video highlights key preparation techniques designed to help minimize air bubbles before the procedure begins.
Watch to review the instruments required, best practices for creating and maintaining negative pressure, and important tips for ensuring the balloon is properly prepared and ready for use.
Because while calcium can be challenging to treat, preparing your Shockwave IVL balloon doesn’t have to be.
Filmed in a demonstration environment. Please ensure adherence to sterile practices. Refer to the Instructions for Use or contact your local representative for further guidance.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
The Shockwave C2 Aero Effect Featuring Dr. Lindsey Cilia and Dr. Allen Jeremias
Join Drs. Lindsey Cilia and Allen Jeremias as they crack into Shockwave C2 Aero’s aero-volutionary deliverability and crossability during an on-site interview at CRT 2026. Watch as they discuss the benefits of this new device compared to prior generations of Coronary IVL, dive into the ways it’s impacted their calcium algorithms, and walk through a calcified tortuous RCA live case performed by Dr Jeremias and his team.
How Has Shockwave Coronary IVL Changed Your Practice? (0:10 -1:15)
Drs. Cilia and Jeremias talk about how safe, effective Coronary IVL has significantly changed the way physicians tackle complex PCI — helping them improve their outcomes especially in complex, tortuous lesions.
Tell Us About Your Experience with Shockwave C2 Aero (1:15-2:15)
Drs. Cilia and Jeremias discuss Shockwave C2 Aero’s device’s improved deliverability, including how it requires less reliance on adjunctive tools compared to Shockwave C2+.
“A lot of times it’s my first go-to device for calcium modification even if the lesion is super tortuous and the imaging catheter won’t cross.”
—Dr. Lindsey Cilia
“It’s an amazing improvement from the first generation — it’s like going from iPhone 1 to iPhone 15.”
— Dr. Allen Jeremias
How Has Shockwave C2 Aero Impacted Your Treatment Algorithm? (2:20-3:15)
From use as an upfront calcium modification tool to helping enable a radial approach in more complex patients, Drs Cilia and Jeremias cover all the advancements Shockwave C2 Aero has brought to their practices.
“My go-to is really to take this device up front as opposed to some of the more high-risk devices.”
—Dr. Lindsey Cilia
“Many times it avoids using atherectomy … and it shortens the procedure and just simplifies it.”
— Dr. Allen Jeremias
Case Review: PCI of Calcified Tortuous RCA (3:15-end)
Dr. Jeremias walks Dr. Cilia through a recent Shockwave C2 Aero case involving a 74-year-old male patient with multiple comorbidities and a heavy coronary calcium burden involving three different morphologies.
Watch to hear their entire conversation about this complex case, including the importance of imaging, reducing patient time on the table, and how Shockwave C2 Aero’s deliverability, crossability and re-wrapability performed in a real-world scenario.
Dr. Jeremias and Dr. Cilia are paid consultants of Shockwave Medical.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
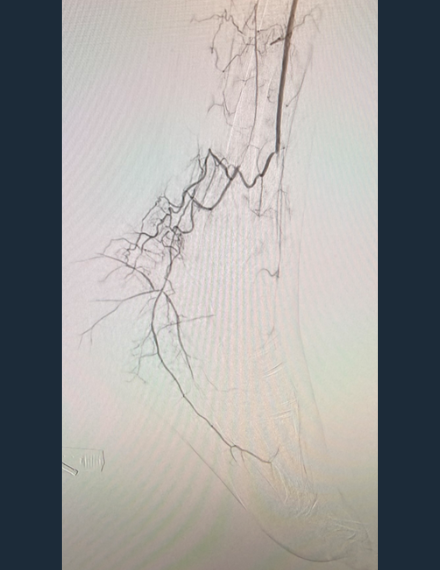
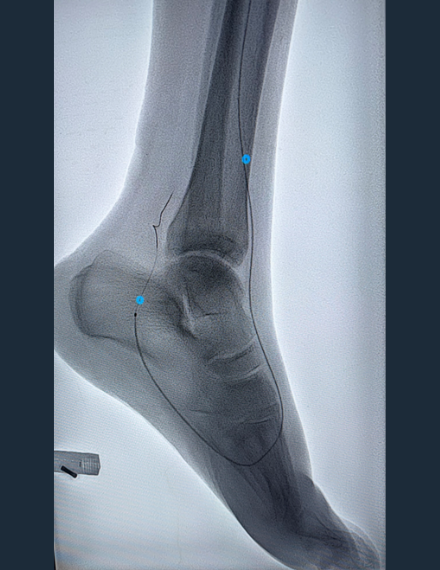
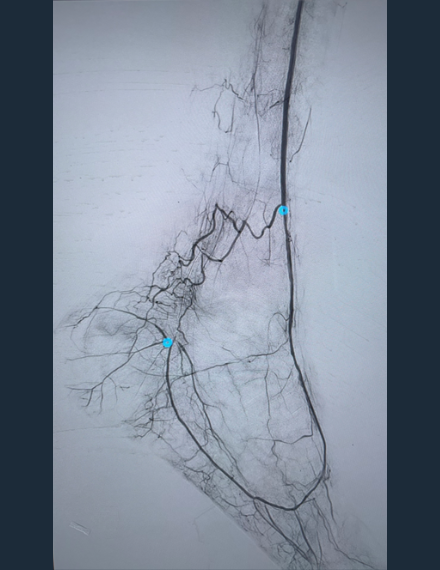
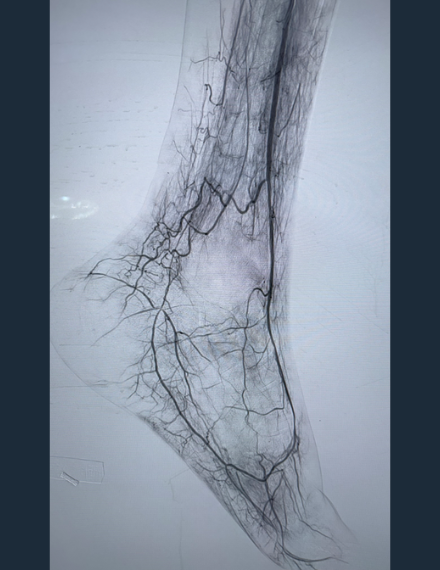
Shockwave Javelin Peripheral IVL Distal Tibial & Below-The-Ankle Case Reviews
At SIR 2026, Dr. Narayanan Thulasidasan, Consultant Interventional Radiologist at Guy’s and St Thomas’ NHS Foundation Trust in London, UK, shares four challenging distal tibial and below-the-ankle (BTA) revascularization cases. These case reviews highlight treatment strategies for heavily calcified disease, procedural decision-making, and the use of Shockwave Javelin Peripheral Intravascular Lithotripsy (IVL) to facilitate successful limb salvage interventions.
Case 1: Distal Tibial & Below-the-Ankle Revascularization Using Shockwave Javelin Peripheral IVL
Dr. Narayanan Thulasidasan presents the treatment of a complex below-the-ankle (BTA) chronic limb-threatening ischemia (CLTI) case in an 86-year-old patient with toe necrosis. Faced with heavily calcified distal pedal disease and limited treatment options, the team used Shockwave Javelin Peripheral IVL to facilitate lesion crossing and vessel preparation, followed by IVL and angioplasty. The case highlights decision-making in challenging distal tibial and pedal interventions and demonstrates successful restoration of blood flow to support wound healing.
Case 2: Complex Pedal Arch Revascularization in a High-Risk CLTI Patient
In this video, Dr. Thulasidasan discusses a challenging below-the-ankle intervention in a patient with diabetes, end-stage renal disease, and tissue loss in a remaining limb. With severe calcification limiting device delivery, Shockwave Javelin Peripheral IVL was used to facilitate crossing and treatment of the dorsalis pedis, pedal arch, and posterior tibial artery. The case highlights procedural strategies for navigating complex pedal anatomy, optimizing lesion preparation, and restoring inline flow to support wound healing and limb preservation.
Case 3: Treating Severe Below-the-Ankle Calcification with Shockwave Javelin Peripheral IVL
Dr. Thulasidasan presents a case involving an 86-year-old patient with a non-healing hallux ulcer caused by a nail bed injury. Faced with extensive calcification and difficult catheter delivery below the ankle, the team used Shockwave Javelin Peripheral IVL to modify calcium in the posterior tibial artery and plantar circulation after conventional crossing techniques proved insufficient. The case highlights procedural decision-making, lesion preparation strategies, and the role of Shockwave Javelin Peripheral IVL in facilitating treatment of heavily calcified distal tibial and pedal vessels to improve perfusion and support wound healing.
Case 4: Urgent Limb Salvage Following Partial Foot Amputation
Dr. Thulasidasan presents a complex Rutherford 5 chronic limb-threatening ischemia (CLTI) case in a patient who required emergency partial foot amputation due to infection and sepsis. With severe below-the-ankle calcification limiting conventional treatment options, Shockwave Javelin Peripheral IVL was used to modify calcium in the posterior tibial and plantar arteries, enabling successful balloon delivery and revascularization. The case highlights the role of Shockwave Javelin Peripheral IVL in overcoming heavily calcified distal disease, restoring blood flow after urgent surgical intervention, and supporting ongoing wound healing.
Dr. Thulasidasan is a paid consultant of Shockwave Medical.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
2026 OBL Reimbursement Updates: Understanding the New IVL Add-On Code
Shockwave partnered with Outpatient Endovascular & Interventional Society (OEIS) for an educational webinar focused on 2026 office-based labs (OBL) reimbursement updates and the new intravascular lithotripsy (IVL) add-on code. This series includes practical case billing examples and expert perspectives on real-world reimbursement in the OBL.
Speakers:
Dr. Bret Wiechmann
Executive Committee, OEIS
Medical Director, Vascular & Interventional Physicians
Teri Yates
CEO, Accountable Physician Advisors
Moderator:
Dr. Bob Tahara
Executive Committee, OEIS
Director, Allegheny Vein & Vascular
Chapter 1: IVL in the OBL Reimbursement Overview
Teri Yates provides an overview of IVL reimbursement in the OBL, including 2026 updates and key coding changes impacting peripheral revascularization procedures.
Chapter 2: IVL in the ASC Reimbursement Overview
Teri Yates reviews IVL reimbursement coding in the ASC setting.
Chapter 3: OBL Clinical Scenario Examples
Dr. Bret Wiechmann walks through example OBL cases, reviewing associated coding, use of IVL add-on codes, and estimated reimbursement outcomes.
Chapter 4: Real World OBL Reimbursement Experience
Teri Yates walks through real-world OBL reimbursement examples and how IVL procedures are being paid. Drawing on her expertise in OBL billing and coding, she shares practical guidance for navigating reimbursement and addressing payer challenges.
Chapter 5: IVL in the OBL Reimbursement Summary
Dr. Wiechmann summarizes the reimbursement takeaways, including IVL add-on codes and payment rates in the OBL.
Dr. Bret Wiechmann and Teri Yates are paid consultants of Shockwave Medical.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
In this case, Dr. Jeff Tyler, MD (Orange County Heart Institute, Director of Cardiogenic Shock at Providence St. Joseph Hospital), takes on a severely stenosed lesion that initially resisted intravascular ultrasound (IVUS) crossing. Shockwave C2 Aero demonstrates its enhanced deliverability and crossability, successfully navigating the lesion where traditional imaging tools could not.
By overcoming these procedural barriers, Shockwave C2 Aero helps simplify an otherwise extremely difficult intervention and enables treatment in a case that would typically present significant limitations.
Watch the case review to learn more.
Dr. Tyler is a paid consultant of Shockwave Medical.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
Shockwave C2 Aero Helps Facilitate Successful Revascularization of Complex Left Main Bifurcation — Dr. Yousif Ahmad and Dr. Brett Wanamaker
Curious how Shockwave C2 Aero performs in tough, calcified lesions? In this case review, Dr. Yousif Ahmad and Dr. Brett Wanamaker take you step‑by‑step through an initial Rotashock procedure, demonstrating how Shockwave C2 Aero’s enhanced deliverability and crossability help safely increase vessel compliance before stenting.
Patient Overview: Complex Calcified Left Main Bifurcation
An 85-year-old female patient presented with worsening angina and dyspnea. Angiography showed severely calcified distal left main bifurcation disease, impacting both the left anterior descending artery (LAD) and diagonal branches.
Deploying Shockwave C2 Aero Post-Atherectomy to Increase Compliance Before Stenting
Dr. Ahmad used atherectomy in the LAD and circumflex, resulting in a slow flow complication in the LAD that was resolved with bailout stenting. He followed with a 4.0 mm Shockwave C2 Aero catheter to achieve complete calcium modification. Dr. Ahmad first delivered 60 pulses in the left circumflex artery (LCX), then advanced the catheter easily into the proximal LAD lesion to deliver the remaining 60 pulses. Finally, he placed a stent in the left main bifurcation.
Post-Case Reflection: Next-Gen Capabilities Could Enable Shockwave IVL-First Strategy
Dr. Ahmad and Dr. Wanamaker discuss how Shockwave C2 Aero’s upgrades — increased deliverability, crossability and re-wrap ability — in conjunction with Shockwave’s proven safety and efficacy have the potential to shift workflows to a Shockwave IVL-first approach.
Watch the full case review to learn more about Shockwave C2 Aero’s capabilities in complex coronary interventions.
Dr. Ahmad and Dr. Wanamaker are paid consultants of Shockwave Medical.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
Enhanced Deliverability with Shockwave C2 Aero in Complex Coronary Lesions with Dr. Brett Wanamaker
Dr. Brett Wanamaker, MD, FACC, FSCAI, Associate Professor of Internal Medicine at the University of Michigan, presents a Shockwave C2 Aero case demonstrating improved deliverability and crossability in complex calcified coronary lesions.
Treating Complex Calcified LAD and RCA CTO Lesions
This case highlights treatment of a severely calcified left anterior descending artery (LAD) and a right coronary artery (RCA) chronic total occlusion (CTO). The Shockwave C2 Aero successfully crossed a tortuous proximal LAD and the RCA CTO with minimal guidewire or catheter support, demonstrating strong lesion crossing capability in challenging anatomy.
Overcoming Failed Stent Delivery
Although noncompliant balloons were able to cross both lesions, initial stent delivery attempts were unsuccessful—highlighting the limitations of conventional approaches in heavily calcified lesions.
Enabling Stent Delivery with Calcium Modification
Following calcium modification with Shockwave C2 Aero, stent delivery was achieved. Final imaging confirmed strong stent expansion with a high minimal stent area (MSA), supporting a favorable procedural outcome and positive patient prognosis.
Watch the full case review to see how Shockwave C2 Aero improves crossability, enables stent delivery, and optimizes outcomes in complex calcified coronary lesions.
Dr. Wanamaker is a paid consultant of Shockwave Medical.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
Moving Calcium Modification Forward: Shockwave Javelin Case Review
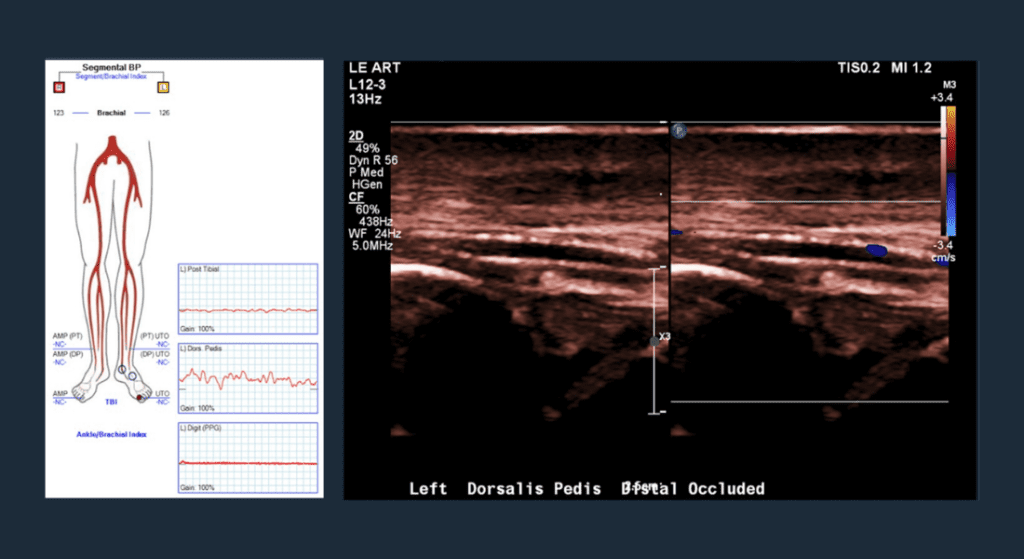
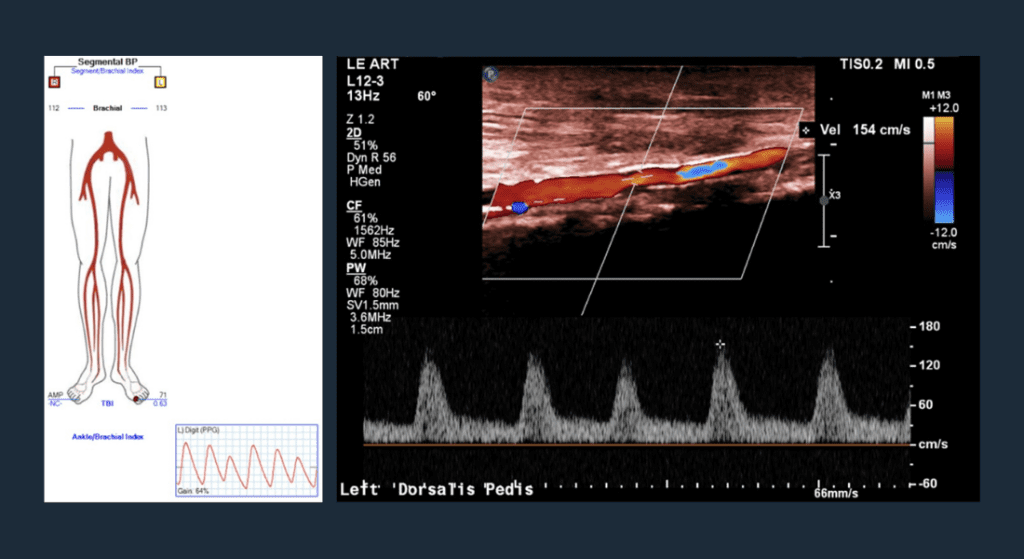
Shockwave Javelin helps expand your treatment options across calcified peripheral lesions. Dr. Charles Bailey, Emory University Hospital, used Shockwave Javelin in the anterior tibial (AT), dorsalis pedis (DP) and pedal-plantar loop of a 67-year-old male patient suffering from left foot nocturnal rest pain and a recurrent toe ulceration. His medical history included diabetes mellitus, hypertension, congestive heart failure and a prior femoral-to-proximal AT prosthetic bypass graft. Revascularization goals included improved forefoot perfusion and improved outflow tract for long-term graft durability.
Pre-Procedure Angio
Occlusive calcium in AT extending into DP
Shockwave Javelin Treatment Angio
120 pulses delivered across occlusive segments
Post-Shockwave Javelin Angio
Restored patency to distal AT, DP and pedal-plantar loop
Final Angio
Brisk flow restored throughout treated vasculature
Pre-procedural vascular testing showed absent great-toe pressure, occlusion of the distal anterior tibial and dorsal pedal arteries, and a patent but low-velocity bypass graft with poor distal outflow consistent with chronic limb-threatening ischemia. The distal AT and DP lesions were traversed intraluminal and Shockwave Javelin was used to modify the heavily calcified plaque followed by a percutaneous transluminal angioplasty (PTA) balloon.
Peri-procedural management included systemic heparinization with activated clotting time (ACT) >> 250 seconds and use of low-profile crossing and support catheters to protect the bypass while optimizing outflow to improve graft-assisted patency.
Post-operatively, Dr. Bailey continues to monitor the patient’s restored distal perfusion, wound healing and graft patency while optimizing medical comorbidities to preserve limb salvage and long-term graft durability.
Pre-op Vascular Lab Testing
No great toe pressure; dorsal pedal occlusion.
Post-op Vascular Lab Testing
Great toe pressure restored to 71mmhg; widely patent dorsal pedal vessel.
Dr. Bailey is a paid consultant of Shockwave Medical.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
Superficial Femoral–Popliteal Occlusion Treated With Shockwave IVL and Stenting
A male patient presents with short-distance, lifestyle-limiting claudication of the left lower extremity (LLE) and having failed an exercise program.
Using a contralateral approach to access the the LLE, Dr. Foteh successfully crosses the lesion and advances the Shockwave E8 6.0 mm x 80 mm catheter delivering all 400 pulses. Dr. Foteh deploys a series of stents and post-dilates with a PTA balloon, resulting in a widely patent superficial femoral artery with distal reconstitution of the popliteal artery. The case exhibits no dissections or embolic complications.
Dr. Foteh is a paid consultant of Shockwave Medical.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
Critical Limb Ischemia: Right Anterior Tibial & Dorsalis Pedis Revascularization Using Shockwave Javelin
Dr. Foley presents an 84 year-old male with history of heart failure, hypertension, diabetes, high cholesterol, non compressible ankle-brachial index (ABI), toe-brachial index (TBI) 0.3, limb threatening ischemia with a left hallux ulcer.
From an antegrade approach, Dr. Foley delivers 40 pulses from Shockwave Javelin to modify the focal peroneal lesion and enable crossing. This was followed by a 3.5mm x 40 mm PTA balloon, resulting in an impressive gain with IVL therapy with no dissections or embolic complications.
Dr. Foley is a paid consultant of Shockwave Medical.
Shockwave IVL: In the U.S.: Rx only. Prior to use, please reference the Important Safety Information for more information on indications, contraindications, warnings, precautions and adverse events.
You are about to exit for another Shockwave Medical country or region-specific website.
Please be aware that the website you have requested is intended for the residents of a particular country or region, as noted on that site. As a result, the site may contain information on medical devices that are not approved in other countries or regions. Do you wish to continue and exit this site?